TESTOSTERONE HEALTH
When it comes to testosterone replacement therapy (TRT), the route of injection can influence convenience, comfort, testosterone levels, and potentially the peak-to-trough pattern of hormone exposure. But is subcutaneous testosterone actually as effective as an intramuscular injection?
The answer appears to be yes for many patients.
Intramuscular testosterone injections have been the traditional approach to injectable TRT for decades. However, an increasing body of research suggests that subcutaneous testosterone injections can also reliably produce therapeutic testosterone concentrations, while offering some patients a smaller needle, easier self-administration, and greater comfort.
Importantly, the available evidence does not show that SubQ testosterone is universally superior to IM testosterone.
Instead, the research suggests that both routes can work, and the best option depends on the testosterone formulation, dose, injection frequency, patient preference, injection volume, laboratory results, and individual response.
At Valyr Health, we believe TRT should be individualized rather than treating every patient according to a one-size-fits-all protocol.
What Is the Difference Between Subcutaneous and Intramuscular Testosterone?
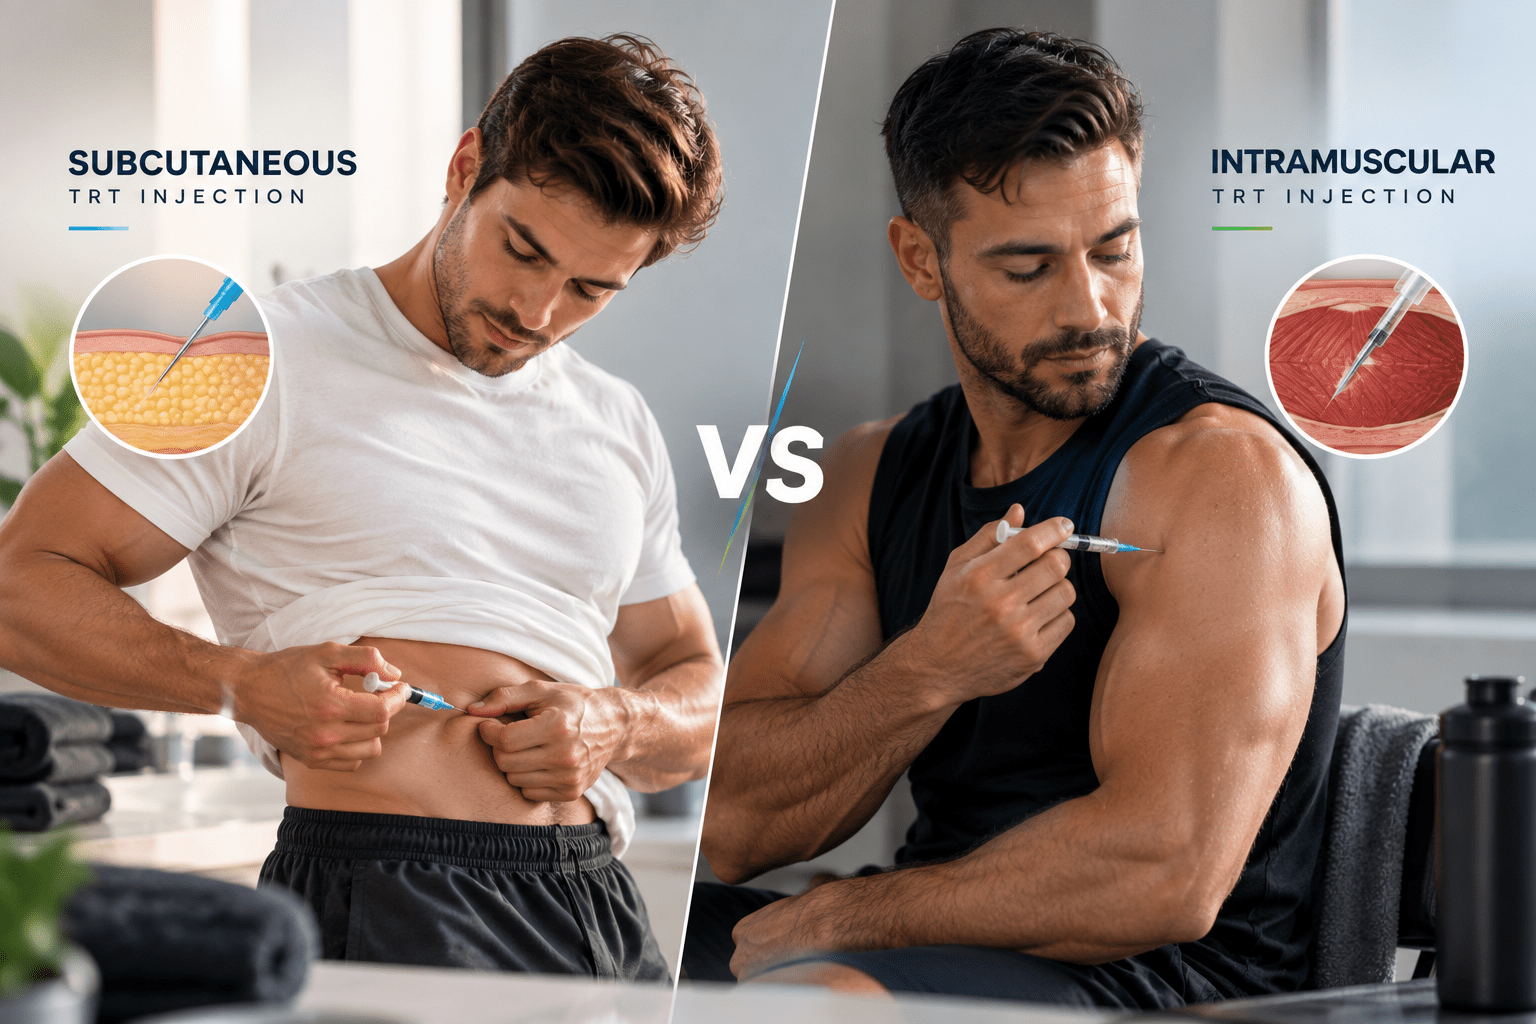
The difference is primarily where the testosterone is deposited.
Intramuscular testosterone
An IM injection places testosterone into muscle tissue.
Common injection sites include:
- Gluteal muscle
- Vastus lateralis/thigh
- Deltoid muscle
Because the medication is deposited deeper in the body, IM injections generally require a longer needle.
Subcutaneous testosterone
A SubQ injection places testosterone into the fatty tissue immediately beneath the skin.
Common sites include:
- Abdomen
- Thigh
- Flank
SubQ injections typically use a shorter, smaller-gauge needle.
The important question is whether testosterone injected into fat tissue can reach the bloodstream effectively.
The research says yes.
Does Subcutaneous Testosterone Actually Work?
One of the most important studies addressing this question was published in the Journal of Clinical Endocrinology & Metabolism.
Spratt and colleagues studied 63 transgender men receiving weekly testosterone cypionate or testosterone enanthate by subcutaneous injection.
Patients received doses ranging from 50–150 mg per week, adjusted according to serum testosterone levels.
The results were significant:
All 63 participants achieved testosterone concentrations within the normal male range.
The median weekly doses were approximately 75–80 mg.
The study also found that SubQ testosterone was effective across a wide range of body mass indexes, from 19.0 to 49.9 kg/m².
Of the 22 patients who had previously been receiving IM testosterone and switched to SubQ administration, all preferred the SubQ injections, with 20 describing a marked preference.
Read the full PubMed article: Spratt et al., 2017
Why does this study matter for TRT?
This was not a study of hypogonadal cisgender men, so it should not be treated as direct evidence that every man with hypogonadism will respond identically.
However, the study provides useful evidence that testosterone cypionate and enanthate can be effectively absorbed through the subcutaneous route and produce testosterone concentrations in the male physiologic range.
That pharmacologic finding is relevant when considering SubQ testosterone for TRT.
Direct Evidence in Men With Hypogonadism
Even more compelling for traditional TRT is a 2022 study that directly compared two testosterone injection approaches in 234 hypogonadal men.
The investigators compared:
- 100 mg weekly intramuscular testosterone cypionate
- 100 mg weekly subcutaneous testosterone enanthate delivered through an autoinjector
After 12 weeks, both groups experienced substantial increases in trough testosterone.
Intramuscular testosterone cypionate
Average testosterone:
313.6 → 536.4 ng/dL
Subcutaneous testosterone enanthate
Average testosterone:
246.6 → 552.8 ng/dL
Both increases were statistically significant.
Most importantly, after statistical adjustment, the researchers found that the route of testosterone administration was not independently associated with the resulting testosterone level.
Read the full PubMed article: Choi et al., 2022
In other words:
For this study population, 100 mg weekly SubQ testosterone enanthate produced testosterone levels comparable to 100 mg weekly IM testosterone cypionate.
That is one of the strongest pieces of evidence available for men receiving TRT.
SubQ Testosterone and Testosterone Levels
A particularly interesting finding from the 2022 study was that the average trough testosterone levels were remarkably similar:
Treatment
Baseline TT
12-week TT
IM testosterone cypionate 100 mg/week
313.6 ng/dL
536.4 ng/dL
SubQ testosterone enanthate 100 mg/week
246.6 ng/dL
552.8 ng/dL
The study did not find a statistically significant independent association between administration route and post-treatment total testosterone.
This is important because one common concern about SubQ TRT is that testosterone placed into fat tissue might not be absorbed as effectively as testosterone placed directly into muscle.
The available clinical evidence does not support that concern as a general rule.
Does SubQ Testosterone Produce More Stable Testosterone Levels?
This is a more complicated question.
It is tempting to say:
“SubQ testosterone absorbs more slowly, so testosterone levels are automatically more stable.”
The scientific literature doesn’t justify such a blanket statement.
Testosterone levels are influenced by:
- Testosterone ester
- Dose
- Injection frequency
- Injection volume
- Formulation
- Individual metabolism
- Absorption
- Timing of the blood test
The frequency of administration may be at least as important as whether the injection is IM or SubQ.
For example, weekly testosterone injections generally produce less dramatic fluctuations than giving a larger dose every two weeks.
Why Can Testosterone Injections Cause Peaks and Troughs?
Testosterone cypionate and testosterone enanthate are long-acting testosterone esters.
After an injection, testosterone levels rise as the ester is released and metabolized.
Levels subsequently decline before the next injection.
This can create a pattern:
Injection → testosterone rises → peak → gradual decline → trough → next injection
Older pharmacokinetic research illustrates how pronounced this can be with larger, less frequent IM doses.
One study of 11 hypogonadal men receiving 200 mg IM testosterone cypionate found approximately a threefold increase in serum testosterone, with peak testosterone occurring around days 2–5. Testosterone subsequently declined toward baseline by approximately days 13–14. Estradiol also increased during the post-injection period.
Read the full PubMed article: Nankin, 1987
This is one reason clinicians often consider more frequent, smaller injections for patients who experience significant fluctuations.
Is the Injection Route or the Dosing Schedule More Important?
For many patients, both matter.
Changing from IM to SubQ may alter the pharmacokinetic profile, but changing from a large, infrequent dose to smaller, more frequent doses can also substantially reduce peak-to-trough variation.
For example:
200 mg every 2 weeks
can produce:
Large peak → gradual decline → low trough
whereas:
100 mg weekly
generally produces:
Smaller peak → smaller decline → higher trough
And some patients may use even more frequent dosing under clinician supervision.
This doesn’t mean everyone should inject more frequently.
It means that dose and frequency should be considered alongside injection route.
A Study of Weekly SubQ Testosterone Levels
Another important study examined testosterone levels throughout the entire week in patients receiving weekly SubQ testosterone.
Researchers studied 11 transgender men who were already receiving weekly SubQ testosterone cypionate.
Blood samples were collected at eight different points throughout the weekly dosing interval.
The researchers found that mean total and free testosterone concentrations remained relatively stable and within the normal range between injections.
The average testosterone concentration across the seven post-injection samples was:
627 ± 206 ng/dL
with considerable individual variation.
Read the full PubMed article: McFarland et al., 2018
Why is this useful?
This study provides evidence that weekly SubQ testosterone can maintain testosterone exposure across an entire dosing interval.
Again, because the participants were transgender men, this is best viewed as supportive pharmacokinetic evidence rather than a direct TRT trial.
SubQ Testosterone Enanthate Can Maintain Testosterone for a Full Week
There is also direct evidence in hypogonadal men.
A phase II study evaluated a novel SubQ testosterone-enanthate autoinjector in men with hypogonadism.
Participants received weekly doses of:
- 50 mg
- 100 mg
Both doses produced normal average testosterone concentrations across the 168-hour dosing interval.
At steady state, mean testosterone concentrations were approximately:
422 ng/dL with 50 mg
and
896 ng/dL with 100 mg
The researchers described the exposure as dose-proportional and noted relatively low variation throughout the weekly interval.
Read the full PubMed article: Kaminetsky et al., 2015
This is particularly relevant because it demonstrates that SubQ testosterone can provide sustained testosterone exposure across a seven-day interval in men with hypogonadism.
SubQ vs. IM Testosterone: What About Estradiol?
This is an area where the original article was too definitive.
It stated that SubQ testosterone was better at controlling estrogen because it absorbs more slowly.
The evidence doesn’t establish that universally.
However, the 2022 study in 234 hypogonadal men produced an interesting finding.
The SubQ testosterone-enanthate group had lower post-treatment estradiol and hematocrit than the IM testosterone-cypionate group after adjustment for relevant variables.
The investigators found that the SubQ treatment modality was independently associated with:
- Lower estradiol
- Lower hematocrit
while testosterone levels themselves were not significantly different between treatment groups.
That is clinically interesting.
But there is an important limitation:
The study compared different testosterone esters and delivery systems, not simply the same testosterone medication injected by two different routes.
Therefore, we cannot conclude that the difference was caused solely by “SubQ versus IM.”
The formulation and delivery device could also have contributed.
Does SubQ Testosterone Cause Less Erythrocytosis?
Possibly in some formulations and patients-but again, the evidence isn’t strong enough to say that SubQ testosterone universally causes less erythrocytosis.
The 2022 study found significantly lower hematocrit in the SubQ testosterone-enanthate group compared with the IM testosterone-cypionate group.
That is an important finding.
However, the study’s design means we should not automatically attribute the difference to injection depth alone.
Other factors may include:
- Testosterone ester
- Pharmacokinetic profile
- Delivery system
- Peak testosterone concentration
- Patient characteristics
- Dose exposure
Therefore, a scientifically responsible conclusion is:
Some evidence suggests that particular SubQ testosterone formulations may produce lower hematocrit and estradiol levels than certain IM regimens, but more direct head-to-head trials using the same testosterone formulation are needed.
What Does the Transgender Literature Tell Us?
There is substantially more published research on SubQ testosterone in transgender men than there is on direct IM-versus-SubQ testosterone in hypogonadal cisgender men.
That makes transgender studies useful when evaluating the pharmacology of the administration route.
But we should be careful.
Transgender testosterone therapy differs from TRT for hypogonadism in several ways:
- Treatment goals may differ
- Doses may differ
- Patient populations differ
- Baseline hormone concentrations differ
- Treatment duration can differ
- Desired testosterone ranges may differ
Therefore, transgender studies should be used to support pharmacokinetic and administration principles, not to automatically claim identical clinical outcomes in TRT patients.
Study: SubQ Testosterone in Transgender Men
Spratt et al. evaluated 63 transgender patients receiving weekly SubQ testosterone cypionate or enanthate.
All patients achieved testosterone concentrations within the normal male range.
The study also found that SubQ therapy was well tolerated, with only minor transient local reactions reported in 9 of 63 patients.
Interestingly, 22 participants had previously used IM testosterone.
After switching to SubQ:
20 strongly preferred SubQ.
None preferred returning to IM.
This suggests that the practical advantages of SubQ administration may be meaningful to some patients.
Study: SubQ Testosterone in Younger Transgender Men
Another study evaluated 36 transgender adolescents and young adults receiving SubQ testosterone cypionate.
The average weekly dose was approximately 46.4 mg.
After six months:
91.4% achieved testosterone levels within the normal male range.
The average total testosterone was:
521.4 ng/dL
This study further supports the ability of SubQ testosterone cypionate to achieve physiologic male testosterone concentrations.
Read the full PubMed article: Spratt et al., 2016
Again, this population is not equivalent to men receiving TRT for hypogonadism, but it provides additional evidence that testosterone cypionate can be effectively administered subcutaneously.
What About SubQ Testosterone Undecanoate?
An interesting randomized crossover study evaluated testosterone undecanoate given either SubQ or IM.
The study included:
- 11 hypogonadal men
- 9 transgender men
Participants received 1,000 mg testosterone undecanoate by either route.
Researchers evaluated pharmacokinetics, pain, acceptability, and patient preference.
Read the full PubMed article: Spratt et al., 2019
Interestingly, pain was somewhat greater 24 hours after SubQ administration, although the two routes were considered similarly acceptable.
This illustrates an important point:
SubQ isn’t guaranteed to be less painful for everyone.
The experience depends on the medication, injection volume, tissue characteristics, and individual patient.
Does a Smaller Needle Really Matter?
For many patients, yes.
One of the practical advantages of SubQ testosterone is that it generally allows a shorter needle because the medication does not need to reach muscle.
That can be particularly helpful for patients who:
- Have needle anxiety
- Self-inject
- Have difficulty reaching an IM injection site
- Experience muscle soreness
- Prefer a less intimidating injection
The 2017 Spratt study found that patients who switched from IM to SubQ overwhelmingly preferred the SubQ method.
However, patient preference should not be interpreted as proof that SubQ produces better testosterone levels.
It demonstrates something different:
The delivery method may improve treatment acceptability and convenience.
And that matters because adherence is an important part of successful TRT.
Can SubQ Testosterone Be Injected With an Insulin Syringe?
Some testosterone protocols can be administered using small-volume syringes and small-gauge needles.
However, this depends on:
- Testosterone concentration
- Injection volume
- Medication viscosity
- Syringe type
- Needle size
- Prescribed route
Patients should follow the equipment and technique recommended by their clinician.
A smaller needle can make injection more comfortable, but if it takes an excessively long time to draw or inject an oil-based medication, another needle size may be more practical.
Is SubQ Testosterone Absorbed More Slowly Than IM Testosterone?
This is one of the most commonly repeated claims about SubQ TRT.
The answer is:
It can be, but the evidence does not support treating this as a universal rule.
The rate of testosterone absorption depends on much more than whether the medication is deposited into muscle or fat.
It can be influenced by:
- Testosterone ester
- Oil vehicle
- Injection volume
- Tissue characteristics
- Blood flow
- Dose
- Injection frequency
- Individual metabolism
The pharmacokinetic profile of a particular SubQ product may differ from an IM product, but we should not assume that every SubQ testosterone injection produces a slower release.
Does SubQ Testosterone Produce Lower Peaks?
Some formulations appear to.
The SubQ testosterone-enanthate autoinjector was specifically developed to provide a relatively controlled testosterone exposure across the weekly dosing interval.
The phase II study found normal average testosterone concentrations throughout the 168-hour dosing interval with relatively low variation.
However, this should not be generalized to every SubQ testosterone preparation.
A compounded testosterone cypionate formulation administered SubQ may behave differently from a commercial testosterone-enanthate autoinjector.
What About IM Testosterone Peaks?
Large, infrequent IM injections can produce substantial peaks.
As mentioned above, a study of 200 mg IM testosterone cypionate found that testosterone rose approximately threefold, with peak concentrations occurring approximately 2–5 days after injection before declining toward baseline.
Another study examining injectable testosterone enanthate found that 200 mg IM produced eugonadal testosterone levels for approximately 11 days in hypogonadal men.
Read the full PubMed article: Sokol et al., 1982
This helps explain why injection frequency can have such a profound effect on how a patient feels.
SubQ vs. IM Testosterone: A Practical Comparison
Feature
Subcutaneous
Intramuscular
Injection depth
Under skin
Into muscle
Typical needle
Shorter/smaller
Longer
Self-administration
Often easier
Can be more difficult
Muscle soreness
Generally avoided
Possible
Injection-site reaction
Possible
Possible
Testosterone absorption
Effective
Effective
Testosterone levels
Can reach therapeutic levels
Can reach therapeutic levels
Peak/trough variability
Depends on formulation & schedule
Depends on formulation & schedule
Larger injection volumes
May be less practical
Often more practical
Patient preference
Often preferred by some patients
Preferred by some patients
Evidence in hypogonadal men
Growing
Extensive
Evidence in transgender patients
Substantial
Extensive
Monitoring required
Yes
Yes
Is SubQ Testosterone Better Than IM Testosterone?
Not universally.
The strongest evidence supports a more balanced conclusion:
SubQ testosterone is a legitimate and effective alternative to IM testosterone for many patients.
It may be particularly attractive for patients who:
- Prefer smaller needles
- Self-administer their TRT
- Have injection anxiety
- Experience significant muscle soreness
- Want a potentially easier injection routine
IM testosterone may be preferable when:
- Larger injection volumes are required
- The patient tolerates IM injections well
- The formulation is specifically intended for IM use
- The patient’s current protocol is effective and well tolerated
What Does the Research Say About Testosterone Levels?
This is perhaps the most important takeaway.
Study 1: 234 hypogonadal men
IM testosterone cypionate:
313.6 → 536.4 ng/dL
SubQ testosterone enanthate:
246.6 → 552.8 ng/dL
No significant independent difference in post-treatment testosterone levels was found based on treatment modality.
Study 2: Hypogonadal men receiving SubQ testosterone enanthate
50 mg weekly: approximately 422 ng/dL mean steady-state testosterone
100 mg weekly: approximately 896 ng/dL mean steady-state testosterone
Both maintained normal average testosterone concentrations across a 168-hour dosing interval.
Study 3: Transgender men receiving SubQ testosterone
All 63 participants achieved testosterone concentrations within the normal male range.
Study 4: Transgender men receiving weekly SubQ testosterone
Testosterone concentrations remained relatively stable across the weekly dosing interval.
Taken together, these studies provide strong evidence that subcutaneous testosterone can produce therapeutic testosterone levels.
Does Injection Frequency Matter More Than Injection Route?
For some patients, it may.
Consider two hypothetical protocols:
Protocol A: 200 mg IM every two weeks
versus
Protocol B: 100 mg weekly SubQ
The difference between those protocols is not simply IM versus SubQ.
It is also:
Large dose vs. smaller dose
and
Every 14 days vs. every 7 days.
Therefore, it would be inappropriate to attribute every difference in testosterone levels or symptoms solely to injection route.
This is an important distinction when interpreting TRT research.
Could More Frequent Injections Reduce Testosterone Fluctuations?
Potentially.
Smaller, more frequent doses generally reduce the amount of testosterone delivered at any one time.
For example:
200 mg every 2 weeks
could result in larger peaks and lower troughs than:
100 mg every week
And a weekly dose can theoretically be divided further under clinician supervision.
However, there is no single dosing schedule that is best for every patient.
The goal is to achieve appropriate testosterone exposure without unnecessarily increasing total testosterone dose.
What Should You Monitor on TRT?
Regardless of whether testosterone is administered IM or SubQ, monitoring remains important.
Your clinician may evaluate:
Total testosterone
Measures the overall concentration of testosterone in the bloodstream.
Free testosterone
Represents the fraction of testosterone that is not tightly bound to proteins.
SHBG
Sex hormone-binding globulin affects how testosterone is distributed between bound and free forms.
Estradiol
Estradiol is an important hormone in men as well. Symptoms and laboratory results should be interpreted together.
Hematocrit and hemoglobin
Testosterone therapy can increase red blood cell production in some patients.
PSA
Appropriate prostate monitoring depends on age, risk factors, symptoms, and clinical history.
Lipid profile
Cholesterol and triglycerides may be monitored as part of overall cardiovascular risk assessment.
Does the Timing of Your Blood Test Matter?
Absolutely.
This is one of the most overlooked issues when interpreting TRT laboratory results.
If a patient injects testosterone weekly, a blood test immediately after an injection may produce a very different result from a test taken immediately before the next injection.
Therefore, testosterone laboratory results should always be interpreted in relation to:
- Dose
- Injection frequency
- Testosterone ester
- Route
- Time since last injection
A “high” testosterone level without knowing when the injection occurred may be difficult to interpret.
Similarly, a “low” testosterone level drawn immediately before the next injection may represent a trough rather than the patient’s average exposure.
What If You Feel Great After Your Injection but Worse Before the Next One?
This may suggest that your testosterone concentration is fluctuating substantially across the dosing interval.
It does not automatically mean you need to switch from IM to SubQ.
Other possibilities include:
- Increasing injection frequency
- Dividing the dose
- Adjusting the total weekly dose
- Changing the testosterone ester
- Changing the injection route
- Reviewing estradiol
- Reviewing hematocrit
- Evaluating sleep and other health factors
The appropriate solution depends on the individual patient.
What If SubQ Testosterone Causes a Lump?
Small temporary lumps can occur with SubQ injections.
Possible contributors include:
- Injection volume
- Injection speed
- Needle size
- Medication concentration
- Oil vehicle
- Injection site
- Repeated use of the same site
A small, temporary lump does not necessarily mean that testosterone isn’t being absorbed.
However, persistent pain, significant swelling, redness, warmth, drainage, fever, or worsening symptoms should be evaluated by a medical professional.
Can You Switch From IM to SubQ Testosterone?
For appropriate patients, yes.
But the switch should be made with clinician guidance.
Your provider may need to consider:
- Testosterone ester
- Concentration
- Total dose
- Injection volume
- Frequency
- Injection site
- Needle selection
- Testosterone levels
- Hematocrit
- Estradiol
- Symptoms
Importantly, switching the route does not necessarily require changing the total weekly dose.
The 2022 study, for example, compared 100 mg weekly IM testosterone cypionate with 100 mg weekly SubQ testosterone enanthate and found similar resulting testosterone levels.
However, because the formulations were different, clinicians should not assume that every patient can simply change routes on a milligram-for-milligram basis.
So Which Is Better: SubQ or IM?
The best answer is:
Whichever method provides appropriate testosterone levels, good symptom control, manageable side effects, and reliable adherence.
For some men, that will be IM.
For others, SubQ may be substantially easier.
And for many patients, the difference between the two routes may be less important than:
dose + injection frequency + formulation + individual response.
The growing literature suggests that SubQ testosterone is not simply a “second-best” alternative to IM administration.
It can be a legitimate testosterone replacement strategy.
The Bottom Line
The scientific literature increasingly supports subcutaneous testosterone injections as an effective alternative to intramuscular testosterone therapy.
A direct study involving 234 hypogonadal men found that both weekly IM testosterone cypionate and weekly SubQ testosterone enanthate substantially increased testosterone levels, with no significant independent difference in post-treatment testosterone concentrations based on treatment modality.
Clinical trials of SubQ testosterone enanthate have also demonstrated the ability to maintain normal average testosterone concentrations across a 168-hour weekly dosing interval in men with hypogonadism.
Studies in transgender men provide additional pharmacokinetic evidence. Weekly SubQ testosterone cypionate or enanthate has been shown to produce testosterone concentrations within the male reference range, and patients who switched from IM to SubQ frequently reported preferring the SubQ route.
The evidence does not, however, support the claim that SubQ testosterone is inherently superior because it always “absorbs slower,” prevents estrogen increases, or produces more stable testosterone levels.
Instead, the evidence suggests that the testosterone formulation, dose, injection frequency, and individual pharmacokinetics all contribute to the resulting testosterone profile.
For some men, SubQ injections offer a meaningful advantage: a smaller needle, easier self-administration, less intimidating injections, and excellent testosterone levels.
For others, IM injections remain a perfectly reasonable and effective option.
At Valyr Health, the goal should not be to choose the injection route that is most popular. The goal should be to choose the route and dosing strategy that produces the best combination of testosterone levels, symptom control, safety, convenience, and long-term adherence for the individual patient.
Frequently Asked Questions
For many patients, yes. A study of 234 hypogonadal men found similar increases in testosterone with weekly IM testosterone cypionate and SubQ testosterone enanthate.
Not necessarily. In the 2022 study of hypogonadal men, the SubQ group reached a mean testosterone level of approximately 553 ng/dL, compared with approximately 536 ng/dL in the IM group. The difference was not statistically significant after adjustment.
The available evidence does not establish that SubQ is universally safer. However, one large comparative study found lower estradiol and hematocrit with a specific SubQ testosterone-enanthate delivery system compared with IM testosterone cypionate.
It can have a different absorption profile, but “SubQ absorbs slower” should not be treated as a universal rule. The testosterone ester, formulation, dose, injection volume, and patient all influence pharmacokinetics.
Not necessarily. One comparative study found lower estradiol with a particular SubQ testosterone-enanthate product, but this does not prove that all SubQ testosterone produces less estradiol than all IM testosterone.
Many patients prefer SubQ injections, and transgender studies have reported strong patient preference for SubQ administration. However, pain varies by formulation and patient. A study of testosterone undecanoate actually found greater pain 24 hours after SubQ injection than IM injection, although overall acceptability was similar.
Published studies have demonstrated effective SubQ administration of testosterone cypionate in transgender patients. Whether a particular prescription should be administered SubQ should be determined by the prescribing clinician.
Yes. SubQ testosterone enanthate has been studied directly in hypogonadal men and has demonstrated therapeutic testosterone exposure.
Because the medication is placed beneath the skin rather than into muscle, SubQ injections can generally be performed with shorter needles than IM injections. The exact needle and technique should be determined by the prescribing clinician.
Yes. Larger, less frequent injections can produce larger peaks and lower troughs. More frequent dosing can reduce the amount of testosterone delivered at each injection, potentially reducing peak-to-trough variation.
Neither is universally better. Both can be effective. The appropriate choice depends on the testosterone formulation, dose, injection volume, frequency, patient preference, laboratory results, symptoms, and clinician assessment.
Scientific Sources and Further Reading
Scientific References
1. Choi EJ, Xu P, Barham D, et al.
Comparison of Outcomes for Hypogonadal Men Treated With Intramuscular Testosterone Cypionate Versus Subcutaneous Testosterone Enanthate. Journal of Urology. 2022;207(3):677–683.
Why it’s important: Direct comparison in 234 hypogonadal men. Both approaches increased testosterone substantially; treatment modality was not independently associated with testosterone levels. SubQ therapy was associated with lower estradiol and hematocrit in this study.
PubMed – Full article and abstract
2. Kaminetsky J, Jaffe JS, Swerdloff RS.
Pharmacokinetic Profile of Subcutaneous Testosterone Enanthate Delivered via a Novel, Prefilled Single-Use Autoinjector: A Phase II Study. Sexual Medicine. 2015;3:263–273.
Why it’s important: Direct study in men with hypogonadism showing weekly SubQ testosterone enanthate produced normal average testosterone concentrations across a 168-hour dosing interval.
PubMed – Full article and abstract
3. Spratt DI, Stewart II, Savage C, et al.
Subcutaneous Injection of Testosterone Is an Effective and Preferred Alternative to Intramuscular Injection: Demonstration in Female-to-Male Transgender Patients. Journal of Clinical Endocrinology & Metabolism. 2017;102(7):2349–2355.
Why it’s important: 63 transgender patients received weekly SubQ testosterone cypionate or enanthate. All achieved testosterone concentrations within the male range, and patients who switched from IM overwhelmingly preferred SubQ.
PubMed – Full article and abstract
4. McFarland J, Craig W, Clarke NJ, et al.
Serum Testosterone Concentrations Remain Stable Between Injections in Patients Receiving Subcutaneous Testosterone.
Why it’s important: Testosterone was measured repeatedly across the weekly dosing interval in transgender men receiving weekly SubQ testosterone cypionate, demonstrating relatively stable levels between injections.
PubMed – Full article and abstract
5. Spratt DI, et al.
Subcutaneous Testosterone: An Effective Delivery Mechanism for Masculinizing Young Transgender Men.
Why it’s important: 36 young transgender patients received SubQ testosterone cypionate. 91.4% reached testosterone concentrations within the male reference range, with an average total testosterone of approximately 521 ng/dL.
PubMed – Full article and abstract
6. Nankin HR.
Hormone Kinetics After Intramuscular Testosterone Cypionate. Fertility and Sterility. 1987;47(6):1004–1009.
Why it’s important: Demonstrates the substantial testosterone peak and subsequent decline associated with 200 mg IM testosterone cypionate in hypogonadal men.
PubMed – Full article and abstract
7. Sokol RZ, Palacios A, Campfield LA, Saul C, Swerdloff RS.
Comparison of the Kinetics of Injectable Testosterone in Eugonadal and Hypogonadal Men. Fertility and Sterility. 1982;37(3):425–430.
Why it’s important: Evaluated serum testosterone following IM testosterone enanthate in eugonadal and hypogonadal men and provides useful historical pharmacokinetic data on injectable testosterone.
PubMed – Full article and abstract
8. Spratt DI, et al.
Pharmacokinetics and Acceptability of Subcutaneous Injection of Testosterone Undecanoate. 2019.
Why it’s important: Randomized crossover study comparing SubQ and IM testosterone undecanoate in both hypogonadal men and transgender men, including pharmacokinetic and patient-acceptability outcomes.
PubMed – Full article and abstract
Talk With Valyr Health
A qualified Valyr Health clinician can review your symptoms, laboratory results, medical history, and treatment goals to discuss appropriate next steps.